


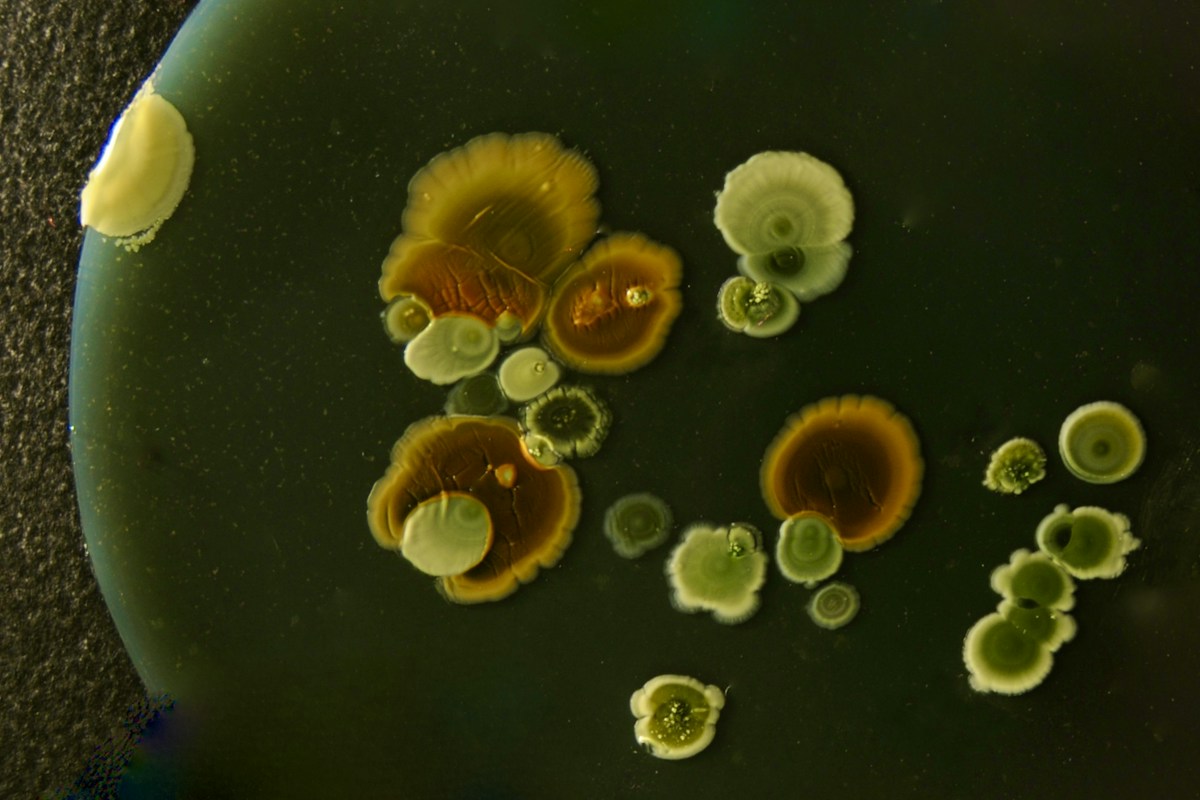
Antimicrobial resistance (AMR) has escalated into one of the most formidable public health emergencies of the twenty-first century, threatening to erode nearly a century of medical progress achieved since the discovery of penicillin. The global dissemination of multidrug-resistant (MDR) and extensively drug-resistant (XDR) bacterial pathogens – particularly carbapenem-resistant Enterobacterales (CRE), multidrug-resistant Pseudomonas aeruginosa, and carbapenem-resistant Acinetobacter baumannii (CRAB) – poses an existential threat to modern healthcare systems, compromising the safety of routine surgical procedures, organ transplantation, and intensive cancer chemotherapy across the globe.
In response to mounting global mortality estimates attributing millions of deaths annually to drug-resistant bacterial infections, international health agencies, regulatory authorities, and infectious disease societies have mobilized aggressive antimicrobial stewardship mandates. These systemic programs seek to optimize clinical antimicrobial prescribing, curb inappropriate antibiotic usage across human and veterinary medicine, accelerate the clinical deployment of next-generation beta-lactamase inhibitor combinations, and implement molecular diagnostic surveillance networks capable of tracking emerging resistance phenotypes in real time.
This comprehensive clinical intelligence report provides an exhaustive, evidence-based analysis of modern antimicrobial stewardship and resistant pathogen surveillance. We detail the molecular enzymology of serine and metallo-beta-lactamases, evaluate the clinical efficacy of novel antibiotic pipelines including siderophore cephalosporins and non-beta-lactam inhibitor combinations, examine cutting-edge rapid microbiological diagnostics such as multiplex PCR and MALDI-TOF mass spectrometry, and outline hospital stewardship implementation frameworks designed to safeguard public health and therapeutic longevity for future generations.
The Escalating Global Crisis of Antimicrobial Resistance: Epidemiological Realities
Antimicrobial resistance represents a silent, accelerating global pandemic characterized by the progressive failure of empirical and definitive antimicrobial regimens against invasive bacterial infections. Systematic epidemiological investigations published in landmark global burden studies estimate that bacterial AMR was directly responsible for 1.27 million deaths in 2019 and contributed to nearly 5 million associated fatalities worldwide, placing AMR mortality on par with major infectious killers such as tuberculosis, malaria, and HIV/AIDS.
The clinical threat is disproportionately concentrated within the ‘ESKAPE’ pathogens – Enterococcus faecium, Staphylococcus aureus, Klebsiella pneumoniae, Acinetobacter baumannii, Pseudomonas aeruginosa, and Enterobacter species. These organisms possess an extraordinary capacity to acquire, express, and horizontally transfer antimicrobial resistance determinants through mobile genetic elements, including plasmids, transposons, and integrons.
Of paramount clinical concern is the rapid global penetration of carbapenem resistance. Carbapenems (meropenem, imipenem-cilastatin, doripenem, and ertapenem) have historically served as the reliable, broad-spectrum antibiotic class of last resort for severe infections caused by extended-spectrum beta-lactamase (ESBL) producing Gram-negative bacilli. The emergence of carbapenem resistance strips clinicians of viable therapeutic options, forcing reliance on toxic, polymyxin-based reserve agents.
Without coordinated global intervention, macroeconomic projections estimate that antimicrobial resistance could cause upwards of 10 million annual deaths by 2050, inflicting a catastrophic toll on global gross domestic product and pushing millions into extreme poverty. Consequently, international healthcare coalitions are enforcing strict antimicrobial stewardship mandates across acute-care hospitals, long-term care facilities, and outpatient ambulatory clinics.
The regional distribution of resistance varies widely across geographic zones, driven by local sanitation infrastructure, antibiotic access without prescriptions, and variable infection control practices. Low- and middle-income countries face the dual burden of high infectious disease incidence and rising resistance rates, highlighting the need for international equity in antibiotic access and molecular diagnostic resources.
Molecular Enzymology of Carbapenemases: KPC, NDM, and OXA-48 Families
Understanding the mechanisms of carbapenem resistance requires examining the molecular enzymology of carbapenem-hydrolyzing enzymes, classified under the Ambler molecular classification system into Class A, Class B, and Class D beta-lactamases. Each class utilizes distinct active site catalytic architectures that dictate its substrate profile and susceptibility to commercial inhibitor agents.
Ambler Class A enzymes are serine beta-lactamases that utilize an active site serine residue (Ser70) to perform a nucleophilic attack on the beta-lactam carbonyl carbon, forming a transient covalent acyl-enzyme intermediate followed by rapid deacylation and ring hydrolysis. The most clinically prominent Class A carbapenemase is Klebsiella pneumoniae carbapenemase (KPC, variants KPC-2 to KPC-50+), encoded on the Tn4401 transposon. KPC efficiently hydrolyzes all penicillins, cephalosporins, monobactams, and carbapenems.
Ambler Class B enzymes represent metallo-beta-lactamases (MBLs), including New Delhi metallo-beta-lactamase (NDM), Verona integron-encoded metallo-beta-lactamase (VIM), and IMP variants. Unlike serine enzymes, MBLs do not form a covalent intermediate; instead, they utilize one or two divalent zinc ions (Zn2+) in their active site to coordinate and activate a catalytic water molecule, generating a nucleophilic hydroxide ion that cleaves the beta-lactam amide bond. Critically, MBLs are completely resistant to all conventional serine beta-lactamase inhibitors, presenting an extraordinary therapeutic challenge.
Ambler Class D enzymes, known as oxacillinases (OXA), are serine beta-lactamases that utilize a unique carbamylated lysine residue within the active site to catalyze beta-lactam hydrolysis. Class D carbapenemases include OXA-48-like enzymes in Enterobacterales and OXA-23, OXA-24/40, and OXA-58 in Acinetobacter baumannii. OXA-48 enzymes exhibit high-level hydrolysis of penicillins and carbapenems but weakly hydrolyze extended-spectrum cephalosporins, often escaping automated microbiological detection.
The rapid dissemination of plasmid-mediated co-resistance is further exacerbated by the co-carriage of 16S rRNA methyltransferases (such as armA and rmtB) alongside carbapenemase genes. This genetic linkage confers high-level pan-aminoglycoside resistance, eliminating aminoglycosides (gentamicin, tobramycin, amikacin) as adjunctive therapeutic choices in severe polymicrobial septic shock.
Clinical Surveillance Networks: Global GLASS and Real-Time Genomic Epidemiology
To counteract the transboundary dissemination of high-consequence resistance genes, global public health bodies have deployed robust, international pathogen surveillance networks. The World Health Organization launched the Global Antimicrobial Resistance and Use Surveillance System (GLASS), standardizing national data collection on AMR in priority human bacterial pathogens across blood, urine, stool, and genital specimens.
In the United States, the Centers for Disease Control and Prevention established the Antibiotic Resistance Laboratory Network (AR Lab Network), connecting regional public health laboratories with state-of-the-art molecular diagnostic technologies. The AR Lab Network provides rapid whole-genome sequencing (WGS), real-time PCR detection of carbapenemase genes, and colonization screening swabs to prevent outbreak clusters within intensive care units and long-term acute care hospitals.
Modern genomic surveillance combines Next-Generation Sequencing (NGS) with bioinformatic phylogenetics to map the global transmission pathways of high-risk bacterial clones. Landmark investigations have tracked the worldwide expansion of Klebsiella pneumoniae sequence type ST258 and ST11 (carrying KPC-bearing plasmids) and Escherichia coli sequence type ST131 (carrying CTX-M-15 and NDM plasmids).
Furthermore, wastewater-based epidemiology (WBE) has emerged as a revolutionary, non-invasive surveillance frontier. By performing shotgun metagenomic sequencing on municipal sewage and hospital wastewater effluents, epidemiologists can detect community-level shifts in resistance gene abundance (the resistome) weeks before resistant infections appear in clinical hospital admissions.
Digital surveillance platforms that integrate automated electronic health record data with local antibiograms now enable infection control teams to detect localized horizontal transmission events within hours. Machine learning predictive models analyze patient movements and shared nursing staff to identify hidden colonization chains before clinical outbreaks manifest.
Novel Beta-Lactamase Inhibitor Combinations: Avibactam, Vaborbactam, and Relebactam
The clinical renaissance in Gram-negative antibacterial therapeutics has been driven by the development of non-beta-lactam beta-lactamase inhibitors, specifically diazabicyclooctane (DBO) and cyclic boronic acid pharmacophores. These innovative molecules overcome the enzymatic degradation that rendered older inhibitors (clavulanic acid, sulbactam, tazobactam) ineffective against modern carbapenemases.
Ceftazidime-avibactam pairs an established third-generation antipseudomonal cephalosporin with avibactam, a synthetic non-beta-lactam diazabicyclooctane inhibitor. Avibactam functions via a reversible carbamylation mechanism, forming a stable covalent acyl-enzyme complex with the active-site serine residue of Class A (KPC), Class C (AmpC), and Class D (OXA-48) beta-lactamases without undergoing hydrolysis. Ceftazidime-avibactam has demonstrated superior clinical cure rates and lower 30-day mortality compared to polymyxin-based therapy for severe KPC and OXA-48 infections.
Meropenem-vaborbactam couples the potent carbapenem meropenem with vaborbactam, a first-in-class cyclic boronic acid beta-lactamase inhibitor. Vaborbactam mimics the tetrahedral transition state formed during beta-lactam hydrolysis, forming a reversible covalent bond between its boron atom and the catalytic serine oxygen of KPC and AmpC enzymes. Because vaborbactam prevents meropenem degradation, this combination restores full meropenem bactericidal potency against KPC-producing Enterobacterales.
Imipenem-cilastatin-relebactam incorporates relebactam, a DBO inhibitor structurally related to avibactam but possessing a piperidine side chain that protects it from active efflux pump extrusion in Pseudomonas aeruginosa. Relebactam potently inhibits KPC and AmpC enzymes, restoring imipenem susceptibility in carbapenem-resistant Pseudomonas aeruginosa isolates that lack metallo-beta-lactamases, significantly expanding the therapeutic armamentarium for nosocomial ventilator-associated pneumonia.
Clinical monitoring during therapy is essential, as mutations in the omega loop of KPC beta-lactamases (specifically D179Y amino acid substitutions) have been reported under prolonged ceftazidime-avibactam monotherapy, conferring resistance to avibactam while paradoxically restoring meropenem susceptibility. This evolutionary dynamic underscores the critical importance of phenotypic re-testing during refractory infections.
Siderophore Cephalosporins: Cefiderocol and the Iron-Trojan Horse Mechanism
The ongoing global spread of Ambler Class B metallo-beta-lactamases (such as NDM and VIM) created an urgent therapeutic void, as avibactam, vaborbactam, and relebactam are chemically incapable of inhibiting zinc-dependent metallo-enzymes. Cefiderocol represents a groundbreaking therapeutic breakthrough designed specifically to overcome metallo-beta-lactamase resistance and porin loss.
Cefiderocol is a synthetic cephalosporin engineered with a unique catechol-type siderophore moiety attached to the 3-position side chain. In nature, bacteria secrete small, high-affinity iron-chelating molecules called siderophores to scavenge scarce ferric iron (Fe3+) from host tissues. Bacterial cell envelopes express specialized outer membrane iron transporter proteins (such as CirA and Fiu in E. coli, and PirA in P. aeruginosa) that actively import ferric-siderophore complexes into the periplasm.
Cefiderocol exploits this essential bacterial nutrition pathway via a biomimetic ‘Trojan horse’ mechanism. The catechol moiety chelates extracellular ferric iron, tricking bacterial iron uptake transporters into actively pumping the antibiotic across the outer membrane into the periplasmic space at high concentrations, bypassing conventional porin channel mutations (such as OmpK35/36 loss) and active efflux pumps.
Once inside the periplasmic space, the cephalosporin core of cefiderocol binds with high affinity to penicillin-binding protein 3 (PBP3), halting peptidoglycan cell wall synthesis and triggering bacterial cell lysis. Crucially, cefiderocol demonstrates extraordinary chemical stability against enzymatic hydrolysis across all major serine and metallo-beta-lactamase classes, including KPC, NDM, VIM, IMP, OXA-48, and OXA-23/24, providing life-saving salvage therapy for refractory carbapenem-resistant Gram-negative infections.
Clinical stewardship guidelines restrict cefiderocol strictly to infections where no other beta-lactam options remain viable, especially given clinical trial data indicating increased all-cause mortality in certain subsets of critically ill patients with Acinetobacter baumannii infections, mandating careful risk-benefit analysis before initiation.
Diagnostic Rapid Microbiology: Accelerating Identification from Days to Hours
Historically, definitive antimicrobial therapy was delayed by 48 to 72 hours while clinical microbiology laboratories performed slow phenotypic blood cultures, subculturing, and automated broth microdilution susceptibility testing. During this vulnerable diagnostic window, patients were treated with empiric broad-spectrum regimens that contributed to antimicrobial selection pressure and worse clinical outcomes.
The integration of Matrix-Assisted Laser Desorption Ionization-Time of Flight Mass Spectrometry (MALDI-TOF MS) has revolutionized bacterial identification. By ionizing bacterial ribosomal proteins from positive blood culture bottles and measuring their time-of-flight to generate a unique spectral mass fingerprint, MALDI-TOF identifies bacterial genus and species with greater than 95 percent accuracy within 15 to 30 minutes of positive culture detection.
Concurrently, multiplex molecular syndromic PCR panels (such as the BioFire FilmArray Blood Culture Identification Panel and GenMark ePlex) simultaneously detect dozens of common bacterial species alongside critical resistance genes directly from positive blood cultures within 60 to 90 minutes. These panels identify blaKPC, blaNDM, blaVIM, blaIMP, blaOXA-48-like, mecA/C (MRSA), and vanA/B (VRE), providing immediate genomic confirmation of resistance mechanisms.
Rapid phenotypic susceptibility systems, including morphokinetic cellular imaging (Accelerate Pheno system), track individual bacterial cell division, morphologic changes, and lysis under antibiotic exposure in real time, delivering true minimum inhibitory concentrations (MICs) within 7 hours. Coupling these rapid diagnostic technologies with active antimicrobial stewardship pharmacist interventions reduces time to effective targeted therapy by an average of 18 to 24 hours, dramatically decreasing patient mortality and hospital length of stay.
Emerging metagenomic Next-Generation Sequencing (mNGS) directly from whole blood and sterile body fluids allows pathogen identification without awaiting blood culture bottle positivity, offering potential diagnosis within 6 to 12 hours for fastidious, slow-growing, or unculturable bacterial pathogens.
Hospital Antimicrobial Stewardship Programs: Core Elements and Metrics
Antimicrobial stewardship programs (ASPs) are multidisciplinary clinical frameworks designed to optimize clinical outcomes, minimize unintended toxicity, curb healthcare costs, and reduce the selective pressure that drives antimicrobial resistance. The Centers for Disease Control and Prevention established the ‘Core Elements of Hospital Antibiotic Stewardship Programs’, providing a gold-standard institutional blueprint.
The core elements comprise seven non-negotiable structural pillars: Hospital Leadership Commitment (dedicated financial, IT, and staffing support); Accountability (appointing a designated physician leader); Pharmacy Expertise (appointing a dedicated infectious disease pharmacist co-leader); Action (implementing prospective audit and feedback, pre-authorization, and facility-specific clinical guidelines); Tracking (monitoring antibiotic prescribing, consumption, and resistance patterns); Reporting (regularly sharing prescribing data with clinical staff); and Education (providing clinical education to clinicians and patients).
Stewardship interventions fall primarily into two operational models: Pre-Authorization (front-end restriction) and Prospective Audit with Feedback (PPAF, back-end review). Pre-authorization requires prescribers to obtain approval from an infectious disease clinician before dispensing high-priority reserve antibiotics (such as carbapenems, ceftazidime-avibactam, or daptomycin), preventing inappropriate empiric overuse.
Prospective audit and feedback involves infectious disease clinicians systematically reviewing active antibiotic orders after 48 to 72 hours of therapy (the ‘antibiotic timeout’). Clinicians review microbiological culture results, evaluate opportunities for de-escalation from broad-spectrum to narrow-spectrum agents, adjust dosages for renal clearance, and switch from intravenous to oral formulations. Quantitative tracking utilizes standardized metrics, notably Days of Therapy (DOT) and Defined Daily Doses (DDD) per 1,000 patient-days, benchmarked via the CDC National Healthcare Safety Network (NHSN) Antimicrobial Use Option.
The integration of clinical decision support systems (CDSS) within electronic health records alerts clinicians to redundant anaerobic coverage, inappropriate double beta-lactam therapy, drug-drug interactions, and missed dose adjustments, preventing medication errors and optimizing stewardship adherence.
Pharmacokinetic/Pharmacodynamic Optimization in Critical Care Infections
In critically ill patients with sepsis and septic shock, altered pathophysiology drastically alters antimicrobial pharmacokinetics (PK) and pharmacodynamics (PD). Sepsis induces endothelial glycocalyx disruption, capillary leak, and third-spacing of fluids, causing massive expansions in the apparent volume of distribution (Vd) of hydrophilic antibiotics (beta-lactams, aminoglycosides, glycopeptides). Simultaneously, augmented renal clearance (ARC, creatinine clearance > 130 mL/min) accelerates antibiotic elimination, frequently resulting in subtherapeutic serum concentrations and treatment failure.
Beta-lactam antibiotics exhibit time-dependent bactericidal killing, wherein clinical efficacy correlates with the percentage of time that free, unbound serum antibiotic concentrations remain above the minimum inhibitory concentration of the infecting pathogen (%fT > MIC). In standard clinical infections, target thresholds are 40 to 70 percent %fT > MIC; however, in critically ill septic patients with high bacterial burdens and elevated MIC pathogens, contemporary clinical guidelines mandate reaching 100 percent %fT > 1-4x MIC.
To achieve these aggressive pharmacodynamic targets without exceeding maximum safe daily dosages, stewardship programs mandate extended (3 to 4-hour) or continuous (24-hour) intravenous infusions of beta-lactams, particularly for meropenem, piperacillin-tazobactam, and cefepime. Continuous infusions eliminate concentration peaks and valleys, maintaining constant, steady-state serum concentrations well above the pathogen’s MIC throughout the entire dosing interval.
Furthermore, Therapeutic Drug Monitoring (TDM) has expanded beyond aminoglycosides and vancomycin to encompass beta-lactams and voriconazole. Real-time chromatographic and immunoassay TDM enables pharmacists to measure circulating trough levels, calculate individual patient clearance rates, and adjust infusion regimens precisely, maximizing bacterial eradication while completely preventing neurotoxic and nephrotoxic complications.
Loading doses are critically required when initiating continuous infusions to immediately saturate the expanded volume of distribution and achieve target therapeutic concentrations within the first hour of therapy, preventing initial subtherapeutic delays in septic shock resuscitation.
The One Health Paradigm: Agricultural Antibiotic Abatement and Ecological Runoff
Antimicrobial resistance cannot be successfully controlled within the human healthcare sector alone; it is intrinsically linked to animal husbandry, veterinary agriculture, aquaculture, and the natural environment. The One Health paradigm recognizes this profound interconnectedness, uniting human medicine, veterinary science, and environmental ecology under a unified global strategy.
Historically, over 70 percent of medically important antibiotics produced globally were consumed in livestock agriculture, not for treating diagnosed animal infections, but as routine, subtherapeutic feed additives for growth promotion and prophylactic herd metaphylaxis. Subtherapeutic antibiotic exposure in poultry, swine, and cattle creates an ideal selective breeding ground for resistant bacterial clones within the animal gastrointestinal microbiome.
Resistant zoonotic pathogens (including multidrug-resistant Salmonella enterica, Campylobacter jejuni, and colistin-resistant E. coli carrying the plasmid-borne mcr-1 gene) are transmitted directly to humans through consumption of contaminated meat products, direct animal contact, or environmental runoff. Furthermore, millions of tons of animal manure containing active antibiotic residues and resistant bacteria are applied as fertilizer to agricultural soil, contaminating surface waterways and groundwater aquifers.
International regulatory frameworks, such as the European Union Veterinary Medicines Regulation and the US FDA Guidance for Industry #213, have instituted mandatory bans on the use of medically important antibiotics for growth promotion and required veterinary prescription oversight for all therapeutic animal feeds. Sustaining these agricultural stewardship mandates and upgrading wastewater treatment facilities to eliminate antibiotic residues are essential prerequisites for containing global AMR expansion.
Aquaculture represents another major ecological interface, where direct dispersion of antibiotics into marine and freshwater systems selects for resistance determinants in aquatic bacteria that can horizontally transfer to terrestrial and human pathogens through plasmid mobilization.
Non-Traditional Therapeutics: Phage Therapy, Monoclonal Antibodies, and Antimicrobial Peptides
Given the slow pace and high economic failure rates of traditional small-molecule antibiotic discovery, biomedical researchers are advancing non-traditional, biological therapeutic modalities that operate via novel bactericidal mechanisms independent of conventional resistance pathways.
Bacteriophage therapy utilizes lytic bacterial viruses (phages) engineered or selected to target specific bacterial species with surgical precision. Phages attach to surface receptors (such as outer membrane proteins or lipopolysaccharide capsular antigens), inject their double-stranded DNA genome, hijack bacterial replication machinery, and synthesize endolysins that rapidly rupture the bacterial peptidoglycan cell wall from within. Clinical trials and emergency expanded access protocols demonstrate successful eradication of refractory biofilms and pan-drug-resistant P. aeruginosa and A. baumannii infections using personalized phage cocktails.
Monoclonal antibodies provide targeted, passive immune clearance of bacterial virulence factors and toxins without inflicting broad-spectrum collateral damage on the protective commensal microbiome. Examples include bezlotoxumab, an FDA-approved monoclonal antibody targeting Clostridioides difficile toxin B to prevent recurrent colitis, and investigational antibodies targeting Pseudomonas elastase and Acinetobacter capsular polysaccharides.
Antimicrobial peptides (AMPs), including defensins and cathelicidins, disrupt bacterial cell membranes via electrostatic interactions with negatively charged bacterial phospholipids, causing membrane permeabilization, pore formation, and rapid osmotic lysis. Researchers are developing synthetic AMP analogues and host-defense peptide mimics with enhanced stability against proteolytic degradation and minimal host cytotoxicity, establishing an innovative frontier in antibacterial drug development.
Fecal microbiota transplantation (FMT) and defined live biotherapeutic products (such as RBX2660 and SER-109) restore intestinal microbial colonization resistance, outcompeting multidrug-resistant enteropathogens and decolonizing intestinal carriage of CRE and VRE.
Economic and Regulatory Incentive Models: The PASTEUR Act and Market Entry Rewards
The global antibiotic pipeline faces a profound economic paradox known as the broken antibiotic market. Developing a novel, first-in-class antibiotic requires hundreds of millions of dollars in preclinical research and rigorous Phase III clinical trials; however, upon receiving regulatory approval, successful antimicrobial stewardship principles dictate that the new drug must be reserved on hospital formulary shelves and utilized only for rare, refractory cases to preserve its long-term efficacy.
Because sales revenues are decoupled from clinical value, numerous innovative biotechnology companies that successfully brought groundbreaking antibiotics to market have filed for bankruptcy or terminated their antimicrobial research divisions. Traditional volume-based pharmaceutical reimbursement models are fundamentally incompatible with effective antimicrobial stewardship.
To correct this systemic market failure, international health economists and legislators have designed ‘pull incentives’, most notably subscription-based reimbursement models often referred to as the ‘Netflix model’ of antibiotic procurement. In the United States, the Pioneering Antimicrobial Subscriptions to End Upsurging Resistance (PASTEUR) Act proposes federal subscription contracts where government agencies pay innovative pharmaceutical developers fixed annual subscription fees for access to novel reserve antibiotics, completely decoupling developer revenue from sales volume.
Similarly, the United Kingdom National Health Service (NHS) piloted the world’s first fully operational antimicrobial subscription payment model, paying fixed annual fees for access to ceftazidime-avibactam and cefiderocol. Expanding these market entry rewards and pull incentives internationally is vital to ensuring that private capital remains committed to replenishing the global antibacterial pipeline before existing reserve agents fail.
Push incentives, supported by global public-private partnerships such as CARB-X and the AMR Action Fund, inject grant funding directly into early-stage preclinical discovery and Phase I trials, de-risking high-attrition early development phases.
Infection Prevention Bundles: Environmental Decontamination and Transmission Interruption
The clinical success of antimicrobial stewardship is inseparable from rigorous, hospital-wide infection prevention and control (IPC) programs. Preventing the horizontal transmission of multidrug-resistant pathogens within healthcare facilities eliminates the initial clinical need for broad-spectrum antimicrobial exposure, functioning as the ultimate preventative stewardship intervention.
Evidence-based infection prevention bundles target transmission interruption through standardized, multi-tiered barrier precautions. For patients colonized or infected with high-priority MDR organisms (such as CRE, CRAB, or Candida auris), hospitals enforce strict Contact Precautions, including dedicated private patient rooms, mandatory donning of clean disposable gowns and gloves upon entry, and dedicated non-critical patient care equipment (such as stethoscopes and blood pressure cuffs).
Environmental surfaces in patient rooms – particularly high-touch objects such as bed rails, call buttons, intravenous pump touchscreens, and bedside tables – frequently harbor resilient bacterial biofilms and bacterial spores. Standard chlorine-based disinfectants or sporicidal hydrogen peroxide formulations must be utilized, with adherence verified through objective fluorescent marking auditing or ATP bioluminescence surface swab assays. Advanced automated adjunct technologies, including pulsed-xenon ultraviolet (UV-C) light decontamination and aerosolized hydrogen peroxide fogging systems, are deployed during terminal discharge room cleanings to eradicate persistent reservoirs.
Furthermore, active surveillance testing (AST) using rectal swabs for CRE or anterior nares swabs for MRSA upon intensive care unit admission identifies asymptomatic carriers, enabling immediate isolation before unseen cross-transmission occurs. Universal chlorhexidine gluconate (CHG) daily patient bathing in intensive care settings has been shown to reduce Gram-negative colonization rates and lower central line-associated bloodstream infections (CLABSIs) by over 30 percent, reinforcing the vital synergy between infection prevention and clinical stewardship.
Hand hygiene compliance auditing via electronic badge tracking systems and direct observation continues to represent the single most cost-effective hospital barrier intervention, directly preventing cross-contamination between consecutive patient beds.
Clostridioides Difficile Prevention: Microbiome Preservation and Fidaxomicin Positioning
A major unintended consequence of broad-spectrum antibiotic therapy is the collateral disruption of the human intestinal microbiome, leading to loss of colonization resistance and secondary proliferation of toxigenic Clostridioides difficile. C. difficile infection (CDI) is recognized as a major hospital-acquired infectious complication, manifesting as severe pseudomembranous colitis, toxic megacolon, sepsis, and high 30-day mortality, especially in elderly and immunocompromised patient cohorts.
Antibiotics exhibiting the highest relative risk for precipitating C. difficile infection include third- and fourth-generation cephalosporins, fluoroquinolones (ciprofloxacin, levofloxacin), clindamycin, and broad-spectrum beta-lactamase inhibitor combinations (piperacillin-tazobactam). These agents indiscriminately decimate protective commensal anaerobic taxa, particularly Bacteroidetes and Clostridium cluster XIVa species, which normally metabolize primary bile acids into secondary bile acids (deoxycholate and lithocholate) that inhibit C. difficile spore germination.
Antimicrobial stewardship interventions aggressively target C. difficile reduction through antibiotic restriction bundles, particularly by replacing high-risk fluoroquinolones with narrow-spectrum targeted alternatives. Clinical studies demonstrate that institutional reductions in hospital-wide fluoroquinolone prescribing correlate with immediate 40 to 60 percent drops in epidemic C. difficile ribotype 027 incidence.
In definitive treatment guidelines issued by IDSA and SHEA, fidaxomicin has superseded oral vancomycin as the preferred front-line therapeutic agent for primary and recurrent CDI. Fidaxomicin is a narrow-spectrum macrocyclic antibiotic that inhibits bacterial RNA polymerase with minimal activity against commensal Gram-negative and anaerobic intestinal flora. By selectively eradicating C. difficile vegetative cells while leaving the protective intestinal microbiome intact, fidaxomicin slashes recurrence rates from 25 percent down to less than 10 percent.
Furthermore, emerging microbiome restoration therapeutics, including FDA-approved orally administered fecal microbiota products (Vowst / SER-109) and rectally instilled biotherapeutics (Rebyota / RBX2660), have established a transformative paradigm for patients suffering from multiple recurrent CDI, permanently repairing intestinal microbial diversity.
Diagnostic Stewardship in Critical Care: Blood Culture Contamination and Biomarker Kinetics
Antimicrobial stewardship cannot succeed without diagnostic stewardship – the practice of ordering the right test, for the right patient, at the right time, and interpreting the results correctly to optimize clinical decision-making. In critical care and emergency departments, diagnostic stewardship targets two rampant clinical pitfalls: blood culture contamination and the over-diagnosis of asymptomatic bacteriuria.
Blood culture contamination, primarily driven by skin commensals such as coagulase-negative staphylococci (Staphylococcus epidermidis), Cutibacterium acnes, and Corynebacterium species, leads to unnecessary hospital admissions, redundant vancomycin prescribing, invasive central venous catheter removals, and extended hospital lengths of stay. Implementing sterile blood culture collection kits, diverter diversion devices that discard the initial 1.5 to 2.0 mL of skin-contaminated blood, and phlebotomy re-training maintains hospital contamination rates below the international benchmark of 1.0 percent.
Serum procalcitonin (PCT) kinetics provide an objective biochemical guide for differentiating bacterial infections from viral illnesses or non-infectious systemic inflammatory response syndrome (SIRS). Procalcitonin is selectively upregulated by bacterial endotoxins and pro-inflammatory cytokines (IL-1b, TNF-alpha) synthesized throughout parenchymal tissues, whereas viral infections stimulate interferon-gamma, which actively suppresses procalcitonin transcription.
Evidence-based procalcitonin algorithms in intensive care guide the early, safe discontinuation of empiric antibacterial therapy. In patients with suspected lower respiratory tract infections or sepsis, when procalcitonin levels drop below 0.25 ng/mL or decline by more than 80 percent from peak values, antibiotics can be safely discontinued without compromising patient survival or clinical cure rates, reducing overall antibiotic exposure by 2 to 4 days per patient.
Similarly, urine diagnostic stewardship programs restrict automatic urinalysis reflexing and mandate clinical criteria before urine cultures are processed. Asymptomatic bacteriuria (ASB) – the presence of bacteria in the urine without localized urinary symptoms – is benign in non-pregnant adults; treating ASB with antibiotics provides zero clinical benefit while actively selecting for resistant uropathogens and increasing C. difficile risk.
Outpatient Antibiotic Stewardship: Acute Respiratory Infections and Delayed Prescribing Models
While high-consequence resistant superbugs proliferate in acute-care hospitals, the sheer volume of global antibiotic selection pressure is overwhelmingly generated in outpatient primary care clinics, urgent care centers, and emergency departments. Epidemiological evaluations reveal that approximately 30 percent of all oral outpatient antibiotic prescriptions are clinically inappropriate, predominantly prescribed for viral acute respiratory infections (ARIs).
Conditions such as acute bronchitis, viral rhinosinusitis, common colds, and non-streptococcal pharyngitis are entirely viral in etiology, yet frequently receive broad-spectrum macrolides (azithromycin) or aminopenicillins secondary to patient expectations, time constraints during clinical visits, and defensive medicine practices. Outpatient antimicrobial stewardship programs implement behavioral ‘nudges’ and communication frameworks that successfully curb inappropriate prescribing.
A highly effective outpatient intervention is the delayed prescription (also termed the ‘wait-and-see’ prescription) model. Clinicians educate the patient on the viral nature of their symptoms, provide symptomatic treatment recommendations, and issue an antibiotic prescription that is post-dated or instructed to be filled only if symptoms worsen after 5 to 7 days. Clinical trials show that over 70 percent of patients never fill the delayed prescription, reporting identical symptom resolution and clinical satisfaction compared to immediate antibiotic recipients.
Public commitment posters displayed in clinic examination rooms – featuring a photograph of the treating physician and a signed statement explaining their commitment to prescribing antibiotics only when truly necessary – have been shown in randomized behavioral trials to reduce inappropriate antibiotic prescribing by 20 percent.
Furthermore, peer comparison auditing, wherein primary care prescribers receive monthly feedback reports ranking their antibiotic prescribing rates against top-performing regional peers, leverages professional social norms to induce long-term, sustained reductions in unnecessary outpatient antibiotic use.
To provide infectious disease specialists, hospital epidemiologists, clinical pharmacists, and healthcare administrators with an evidence-based clinical matrix, the following comparative framework outlines the antimicrobial spectrum, resistance gene coverage, primary clinical indications, and essential stewardship considerations across contemporary reserve antibacterial agents. Each therapeutic agent is classified according to its chemical class, molecular target, and regulatory status.
Applying this structured matrix ensures that hospital clinicians select the most appropriate targeted antibiotic regimen, maximizing patient survival while rigorously safeguarding valuable reserve agents against premature resistance emergence.
| Antibacterial Agent / Class | Inhibitor / Mechanism | Active Resistance Gene Coverage | Primary Clinical Indications | Essential Stewardship Considerations |
|---|---|---|---|---|
| Ceftazidime-avibactam | Diazabicyclooctane (DBO) covalent serine inhibitor | KPC, OXA-48-like, AmpC, ESBLs (NOT active against MBLs) | cIAI, cUTI, HAP/VAP, bacteremia due to CRE/OXA-48 | Reserve for confirmed KPC/OXA-48; monitor for KPC D179Y resistance mutations |
| Meropenem-vaborbactam | Cyclic boronic acid transition-state serine inhibitor | KPC, AmpC, ESBLs (NOT active against OXA-48 or MBLs) | cUTI, pyelonephritis, severe bacteremic KPC infections | Preferred agent for KPC-CRE; ineffective against OXA-48 or metallo-enzymes |
| Imipenem-cilastatin-relebactam | DBO inhibitor with enhanced anti-efflux kinetics | KPC, AmpC, MDR Pseudomonas (NOT active against MBLs/OXA-48) | HAP/VAP, cUTI, cIAI due to resistant P. aeruginosa and CRE | Excellent option for MDR Pseudomonas aeruginosa; renal dosage adjustment critical |
| Cefiderocol | Catechol siderophore cephalosporin Trojan horse | NDM, VIM, IMP (MBLs), KPC, OXA-48, CRAB, Stenotrophomonas | Severe refractory infections due to MBL-CRE or CRAB | Strict pre-authorization; reserve for metallo-beta-lactamases or pan-resistant strains |
| Ceftolozane-tazobactam | Novel cephalosporin with stable PBP affinity + tazobactam | MDR P. aeruginosa (porin loss/efflux), ESBLs (NOT carbapenemases) | HAP/VAP, cUTI, cIAI due to extensively resistant P. aeruginosa | Front-line agent for difficult-to-treat P. aeruginosa; inactive against CRE |
The operational guidelines delineated in the table above emphasize that no single agent provides universal coverage across all multidrug-resistant pathogens. Tailoring antimicrobial therapy requires rapid genomic identification of the specific underlying beta-lactamase enzyme.
Furthermore, implementing strict prospective audit and feedback protocols prevents over-utilization of ultra-broad-spectrum reserve agents like cefiderocol, ensuring that their therapeutic efficacy remains preserved for clinical emergencies.
Frequently Asked Questions About Global Antimicrobial Stewardship
What is the difference between a serine carbapenemase and a metallo-beta-lactamase?
Serine carbapenemases (such as KPC and OXA-48) use an active site serine amino acid residue to cleave the beta-lactam ring and can be inhibited by novel non-beta-lactam inhibitors like avibactam and vaborbactam. Metallo-beta-lactamases (such as NDM and VIM) use zinc ions in their catalytic site, making them completely resistant to serine beta-lactamase inhibitors and requiring specialized agents like cefiderocol or aztreonam-avibactam.
How does the siderophore ‘Trojan horse’ mechanism of cefiderocol work?
Cefiderocol has a synthetic catechol siderophore attached to its side chain that binds to ferric iron. Bacterial iron-transport systems actively pump the iron-bound antibiotic across the outer bacterial membrane into the periplasmic space, bypassing porin mutations and efflux pumps, where it inhibits cell wall synthesis.
Why are extended or continuous infusions used for beta-lactam antibiotics?
Beta-lactams kill bacteria in a time-dependent manner, meaning their success depends on how long the antibiotic concentration stays above the pathogen’s minimum inhibitory concentration (%fT > MIC). Extended (3 to 4 hours) or continuous (24 hours) infusions eliminate drug peaks and troughs, maintaining steady bactericidal levels in critically ill patients.
What are the CDC Core Elements of Hospital Antibiotic Stewardship?
The CDC Core Elements consist of seven pillars: Hospital Leadership Commitment, Accountability, Pharmacy Expertise, Action (interventions like audit and feedback), Tracking (monitoring antibiotic use), Reporting (sharing data with staff), and Education for healthcare workers.
What is the difference between Days of Therapy (DOT) and Defined Daily Doses (DDD)?
Days of Therapy (DOT) measures the number of days a patient receives a specific antibiotic, regardless of the dose. Defined Daily Dose (DDD) is an assumed average maintenance dose per day. DOT is preferred in hospital stewardship because it is not distorted by renal dose adjustments in critically ill patients.
How does rapid diagnostic testing improve antimicrobial stewardship?
Rapid diagnostics like MALDI-TOF mass spectrometry and multiplex molecular PCR panels identify bacterial species and specific resistance genes within 1 to 2 hours of culture positivity, allowing clinicians to switch from broad-spectrum empiric antibiotics to targeted therapy 24 to 48 hours faster.
What is the One Health approach in antimicrobial resistance?
The One Health approach recognizes that human health is inextricably linked to animal health and the environment. It addresses AMR holistically by eliminating subtherapeutic antibiotic use in livestock, preventing agricultural runoff, and upgrading municipal wastewater treatment.
Why did older beta-lactamase inhibitors like clavulanate fail against KPC?
Older inhibitors like clavulanic acid and sulbactam are beta-lactam molecules themselves. Carbapenemases like KPC hydrolyze and destroy these older inhibitors along with the partner antibiotic. Modern inhibitors like avibactam and vaborbactam are non-beta-lactam compounds that bind and neutralize carbapenemases without being destroyed.
What is the PASTEUR Act?
The PASTEUR Act is proposed US federal legislation that creates a subscription-based reimbursement model (‘Netflix model’) for novel antibiotics. The government pays pharmaceutical developers fixed annual subscription fees for access to novel reserve drugs, decoupling revenue from sales volume and revitalizing the antibiotic development pipeline.
How does daily chlorhexidine (CHG) bathing reduce antibiotic resistance?
Daily CHG bathing in intensive care units decontaminates the patient skin microbiome, significantly reducing the density of resistant pathogens like MRSA and CRE. This lowers the incidence of catheter-associated infections and bacteremias, eliminating the need for broad-spectrum antibiotic therapy.
Clinical Perspectives and Future Directions in Antimicrobial Stewardship
Antimicrobial resistance represents a dynamic biological challenge that cannot be resolved through the episodic discovery of novel antibiotics alone. The enduring preservation of modern medicine requires a synchronized, multidisciplinary strategy that unifies rapid molecular diagnostics, sophisticated pharmacodynamic modeling, institutional stewardship governance, and progressive economic incentive models.
By harnessing novel beta-lactamase inhibitor combinations, deploying siderophore antibiotics with surgical precision, and enforcing prospective audit and feedback across all clinical care settings, healthcare systems can stem the tide of multidrug resistance while improving individual patient cure rates and minimizing collateral toxicities.
For accredited institutional consensus and clinical practice guidelines on antimicrobial stewardship and multidrug-resistant pathogen management, clinicians and healthcare executives are encouraged to review clinical guidance documents published by the Infectious Diseases Society of America (IDSA), the European Society of Clinical Microbiology and Infectious Diseases (ESCMID), and stewardship frameworks from the Centers for Disease Control and Prevention Division of Healthcare Quality Promotion. Global epidemiological tracking is continuously cataloged on PubMed National Library of Medicine, alongside international mandates from the World Health Organization Global AMR Action Plan.
